
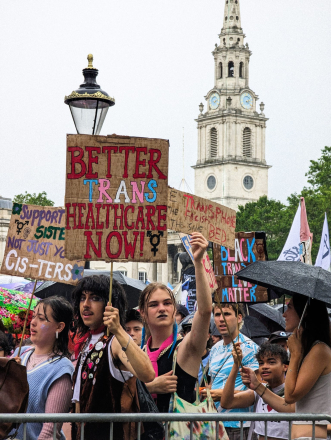
On 13 May in Sheffield, over 300 local GPs, Advanced Nurse Practitioners and other healthcare professionals – plus 80 more online – attended a Protected Learning Initiative (PLI) session focused on the healthcare needs of adult transgender patients.
The trans community is a hugely underserved and undersupported demographic in healthcare. The session aimed to expose and address the vast healthcare inequalities faced by trans patients. It also shared the findings of TransActual’s 2025 Healthcare Professionals Report, in which GPs overwhelmingly reported insufficient training and confidence around transgender healthcare. This lack of confidence was mirrored in the pre-PLI survey of attendees. The session set out to address that.
Lived experience was central to the session. Two of the three presenters were trans or non-binary, one of whom used his own transition to explain how an alternative, informed consent-based model of care could look. The third was one of Sheffield's leading GPs on trans health. Session content was built around Medact’s findings from a survey of Sheffield-based trans people on what they wished their GP knew. A trans woman based in Sheffield spoke in a video about her positive and negative experiences of care. She also warned clinicians against Trans Broken Arm Syndrome, where unrelated health issues are incorrectly assumed to be transition-related.
Trans health was put forward as a PLI topic by a member of Workers’ Liberty through the workplace EDI Champions working group, citing the dire situation for many trans patients. The session was developed through work with Medact Sheffield, and clinicians themselves voted for the topic.
FILLING THE KNOWLEDGE GAPS
The session began by outlining the current situation. Waiting lists to be seen at a Gender Identity Clinic (GIC) are often years or even decades long, while the political context is becoming increasingly hostile. Meanwhile, many healthcare professionals in primary care see gender-affirming care as something they cannot do much to help with due to a lack of specialist knowledge.
It then moved into more practical aspects of care, including how clinicians can support social and legal transition through admin such as providing supporting letters, understanding the difference between deed polls and Gender Recognition Certificates, and understanding screening needs. Medact survey responses demonstrated the impact of both positive and negative experiences on patients.
Concerns around regret popped up a few times in the pre-PLI survey. These were addressed by highlighting the positive impact of gender-affirming hormone therapy (GAHT) on mental health outcomes and social and global functioning, and comparing regret rates for gender-affirming surgery around 1.94% – with those for knee replacements, bariatric surgery, and cancer-related prostatectomy (10–30%). A comparison with the regret rates for marriage and children also helped put these figures in perspective.
The session addressed how to manage the initial GP consultation sensitively and supportively, and the practical aspects of how to refer patients to a GIC and to an NHS endocrinologist (which can speed up access to GAHT if the patient has been given a previous diagnosis of gender incongruence). A few words were shared on due diligence for private clinics – with the gold standard being UK-based, GMC registered, and also working in NHS practice.
Wider aspects of care were also covered, including fertility preservation, contraceptive choices, and additional transition-related interventions such as speech therapy, hair removal, and surgical options beyond what is available on the NHS.
There was also discussion of bridging prescriptions – GAHT prescriptions to ‘bridge’ the long wait between presentation in primary care and being seen at a GIC. Some GPs, depending on practice policy, and only if they feel confident in their knowledge to do so, may be able to issue one if a patient is deemed at risk of resorting to grey market ‘DIY’ hormones, self-harm or suicide. Content included official guidance, medicolegal considerations, hormone counselling and reasons to consider prescribing. Related to this was guidance on supporting and monitoring patients who are already DIYing (self-administering hormones without a prescription).
WHAT NEXT?
To support clinicians to build confidence on an ongoing basis, there is now a trans healthcare resource pack as well as a new clinician peer support network.
Feedback so far has been overwhelmingly positive. Some clinicians described it as the most comprehensive education they have received on trans healthcare. The PLI was a significant step forward.
It is not a silver bullet, though. Systemic challenges with significant barriers to care remain. Gender-affirming care is paid for in years on waiting lists, in private healthcare costs, and/or in health risks from DIYing. This session alone certainly won’t move us away from a system of having to repeatedly ‘prove’ transness in order to access care, nor towards one based upon informed consent. And the fact that this session, which lasted less than two hours, was so highly praised only highlights how sorely lacking trans health education is in primary care contexts.
Addressing these issues would require an overhaul of gender-affirming healthcare in the UK, and the struggle for that must continue. Nonetheless, in the meantime, initiatives like this may help to improve care at a local level. Clinicians in Sheffield will hopefully feel better equipped and more confident to support their patients. For trans patients, this could mean being better understood, more supported, and in some cases having easier access to life-changing care that may otherwise have felt out of reach.
Those working in primary care elsewhere should seek to try and replicate this kind of initiative. As many activists will know, it is surprising what can sometimes happen if you ask the right questions in the right places.
Comments?We welcome replies, corrections and debate pieces. Contact us